💬 General
General
RHTP discussion, implementation experience, and announcements
👍1
💬General
Beyond the Funding: The People Behind Rural Health Transformation
As of October 3, Rural Care Journey reflects: 723 consolidated public opportunities across all 50 states plus federal activity 791 indexed vendors 16,700+ healthcare entities Nearly $1 billion in currently open or closing funding Those numbers are encouraging. But after months of building RCJ, the most important thing I have learned is harder to measure: the people. Behind every opportunity are applicants trying to build something. Behind every vendor profile are people who have spent years solving difficult healthcare problems. Behind every award are clinicians, EMS teams, educators, community organizations, technology companies, and local leaders who ultimately have to make the work succeed. The more conversations I have, the more I believe rural health transformation will depend not only on funding or technology, but also on connecting the right people, building local capacity, and creating relationships that continue after the funding ends. That is increasingly what I want Rural Care Journey to become—not simply a database of opportunities, but a place where people who need help can find people who know how to help. If you work in rural healthcare, are pursuing an RHTP opportunity, or have a capability that could help rural organizations implement one, I hope you will join the conversation here. I shared the longer reflection on Substack: Beyond the Funding: The People Behind Rural Health Transformation
San Lee· 2d ago
2 replies85 views📎 1

👍1
💬General
New: RHTP Market Intelligence — see where the funding is moving
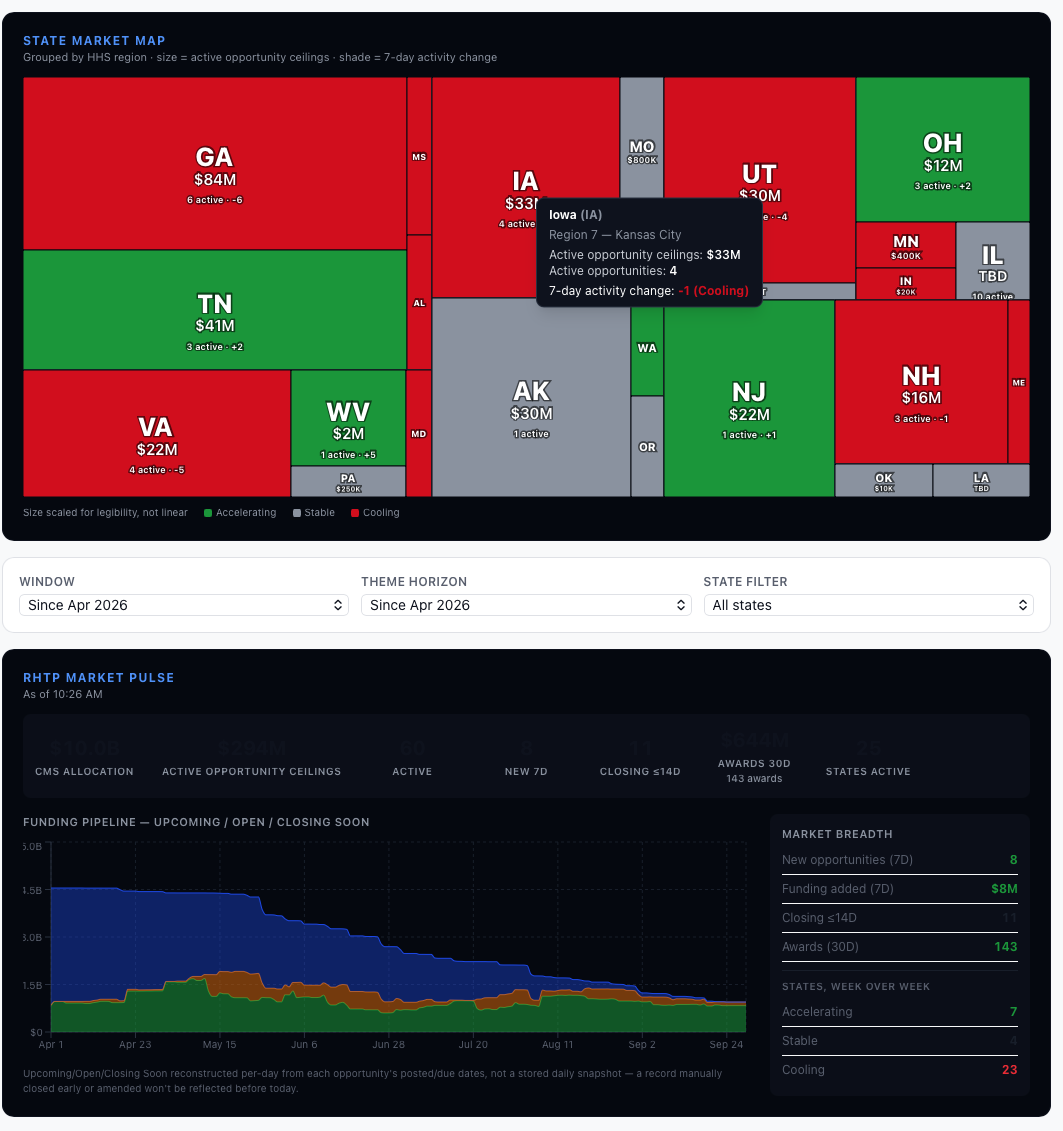
We just launched RHTP Market Intelligence , a live dashboard tracking Rural Health Transformation Program activity across the country: 🔗 View RHTP Market Intelligence What's in it right now: 60 active opportunities across 25 states , worth $294M in currently open/upcoming funding 8 new opportunities posted this week, 11 closing within the next 14 days 143 awards tracked in the last 30 days, totaling $644M A State Market Map , grouped by HHS region, showing at a glance where funding and activity are concentrated Opportunity Movers — newest postings, closing soon deadlines, and recently awarded contracts, in one place Theme Momentum — which RHTP priority areas (telehealth, workforce, care at home, etc.) are picking up Funding Gap — tracked funding per rural resident, state by state This sits alongside the $10B+ in total CMS RHTP allocations we already track nationally — the new board is about the moving parts underneath that: what's open, what's closing, what just got awarded. Filter by state or time window, and it all updates from the same live data as the rest of the site. Would love to hear what you'd want to see next.
RCJ Team· 6d ago
0 replies144 views📎 1
👍1
💬General
ClinEfficiency Pro- Who we are and where we fit into the RHTP initiative
From RHTP Award to Working Model Hello, RHT Community! I’m Dr. Augusta Uwah, an internal medicine physician, former hospitalist and physician advisor, and founder of ClinEfficiency Pro. An award funds a plan. A rural team still has to make that plan work between patient care, staffing constraints, changing policy, and the next reporting deadline. We help rural hospitals turn a funded initiative into a working, measurable service. A practical starting point is one initiative and one focused implementation assessment. We establish the baseline, trace the workflow from decision to delivery, identify who owns each handoff, and define what the team needs to show at its next milestone. The result is a short action plan leaders can use to assign work, resolve gaps, and measure progress. We also support the hospital operations that determine whether transformation can last: Physician advisor and UM capacity: We help teams identify where physician review is most needed, design ways to share limited expertise across sites, and use CLIP to support timely, documented medical necessity and patient status decisions. Policy updates: We translate relevant changes into practical documentation, review, and escalation guidance. AI governance: We help teams set human review, controls, and outcome measures for AI used in clinical and operational work. Clinical and operational leaders keep ownership of care and implementation decisions. Our job is to bring focused physician led analysis and usable tools to the points where capacity is thin and the stakes are high. If you are responsible for moving an RHTP initiative from award to daily practice, I would welcome a conversation. What is the hardest part to make real right now: the workflow, the clinical capacity, or the evidence of results? We would welcome conversations with rural hospitals, health networks, state and regional implementation teams, and partners assembling multidisciplinary RHTP projects. Our strongest fit is an initiative that needs clearer clinical ownership, a workable process, or credible evidence of results. If that is a gap in a project you are building or delivering, please reach out here. I would be glad to compare notes and explore where physician led implementation support could help. Find our rural health engagements at https://clinefficiency.pro/rural health
Augusta· 8d ago
3 replies189 views
👍1
💬General
New RCJ briefing: RHTP Post-Award — What States Must Prove After the Award
CMS's September 2026 Post Award FAQ makes one point especially important: receiving the federal award is only the beginning. States still have to manage Budget Periods, obligations, contracts and subawards, checkpoints, metrics, workforce commitments, policy actions, and ongoing reporting. The new 8 page RCJ briefing translates that guidance into practical questions: How can you tell an open downstream opportunity from a planning signal? What evidence confirms a vendor or subrecipient was actually selected? When can a clinical workforce initiative create a five year rural service obligation? What budget, checkpoint, and recovery risks should vendors watch? Read the briefing: https://www.ruralcarejourney.com/reports/rhtp post award 2026 The official CMS FAQ is also available in Reference Documents. What post award signals are you seeing in your state or market?
RCJ Team· 10d ago
0 replies216 views
👍0
💬General
🧭 Vendor Directory Update: Smarter Search and Organization Filters
Rural Care Journey’s Vendor Directory now makes it easier to discover and compare rural health vendors. New features include: AI powered search with match scores and vendor specific explanations More diverse AI recommendations across vendor categories Organization Type filters: Technology / Software Service Provider Consultant Medical Device / Product Payer / Health Plan Nonprofit Organization Community Based Organization Government / Public Agency Other RHTP Awarded and Logo Only filters Existing vendor cards, profiles, logos, and quote actions retained Keyword search and detailed capability filters remain available Explore the updated Vendor Directory: https://www.ruralcarejourney.com/vendors
RCJ Team· 11d ago
0 replies122 views
👍2
💬General
What Does the RHTP Implementation Network Look Like?
Hello again, RHT Community! As RHTP moves further into implementation, I have been thinking about something we may not see on our project plans: The relationships through which transformation will actually happen. We can identify initiatives, timelines, funding, deliverables, and accountable leaders, but implementation rarely moves through formal structure alone. It also moves through relationships. Who do people trust when something changes? Who do they call when a new process does not work as expected? Who connects clinical, operational, technology, and community partners? Who has influence across departments, or even across organizations, without necessarily having the title? And who is quietly becoming the person everyone depends upon? This is where I believe Organizational Network Analysis (ONA) could offer an important lens for rural health transformation. ONA helps make visible the informal networks through which trust, information, collaboration, knowledge, and influence actually move. Imagine being able to see, during implementation: 1. Where transformation depends heavily on one or two people. 2. Where teams or partners are well connected and where they are not. 3. Who the trusted connectors are. 4. Where information may be getting stuck. 5. Where critical knowledge is concentrated. 6. Where implementation demands may be creating relational overload. This is not about replacing traditional workforce data, surveys, or project management. It is about seeing another layer of the system. We can design an excellent transformation strategy on paper and still miss the human network required to make it work in practice. Perhaps one of our RHTP implementation questions should be: Do we know who is actually carrying the transformation? Perhaps equally important: Do we know whether the network around them is strong enough to sustain it? I would love to hear whether others are thinking about the relational side of RHTP implementation. Thank you! Happy Friday Eve! Sincerely, Ava
Ava Jones, PhD, MSM, RN· 11d ago
4 replies69 views
👍1
💬General
Who We Are and How CerynRx Fits Into RHTP Implementation
CerynRx is a physician supervised, pharmacist led metabolic health company based in Dallas. We built our model around continuous pharmacist oversight verification, counseling, and ongoing monitoring at every step of a patient's treatment rather than the prescribe and ship approach most telehealth platforms run on. That's made us a fit for the areas RHTP programs are already prioritizing: chronic disease prevention, diabetes and obesity care, telehealth, medication management, and care coordination. With Initiative 1 (Make Rural Texans Healthy Again) already awarded roughly $56M in the first competitive round we know districts are moving from planning into actual implementation right now, and medication adherence/persistence is one of the pieces that's easy to underweight against access and enrollment numbers. We're also tracking Initiative 2 (Rural Texas Patients in the Driver's Seat) and Initiative 3 (Lone Star Advanced AI and Telehealth) as those move toward Year 2. You can find our full profile under the Pharmacy & Medication Management capability area if you want more detail on how we work. If you're a district thinking through how a pharmacist first layer fits your Initiative 1 rollout or another vendor working adjacent to this space happy to compare notes here or connect directly.
CerynRx· 12d ago
1 reply166 views
👍2
💬General
🌟 A member story: a first grant-writing experience
We received this thoughtful note from Dusty Lynn after working with the Rural Care Journey team on her organization’s first grant writing experience. I cannot thank you and your team enough for the excellent work you did in guiding us through our first grant writing experience! Your in depth research, expertise, and thoughtful guidance were exactly what we needed to successfully navigate the process and get us across the finish line. We especially appreciated your patience in answering our questions, providing clarification, and helping us understand each step along the way. It is clear that your team has extensive experience with the grant process and is exceptionally well equipped to guide organizations like ours through what can otherwise be an overwhelming undertaking. We are incredibly grateful for your support and look forward to working with you again on our next grant opportunity. I would highly recommend your team to any organization seeking knowledgeable, professional, and supportive grant writing assistance. Thank you again for helping make our first grant writing experience such a positive one!! Looking forward to more collaboration. — Dusty Lynn, RN, M.Sc., LNC, EMT P Neonatal and Pediatric Emergency Education · Legal Nurse Consultant
RCJ Team· 14d ago
1 reply261 views
👍2
💬General
RCJ Community Launch Challenge — Winners
The RCJ Community Launch Challenge closed last night, and we want to thank everyone who posted a question, shared a lesson, or helped someone else find an answer over the past four weeks. Winners — 3 months of RCJ Pro each: Ava Jones, PhD, MSM, RN Aleph Group Inc. Kristin DeProspero Michelle Elam Vendor Network bonus — 1 month of Featured Vendor placement ($300 value): Ava Jones, PhD, MSM, RN (OrgAcuity) We'll be reaching out to each winner directly over the next few days with next steps. Thank you for helping kick off RCJ Community — keep the posts and questions coming, the conversation doesn't stop here.
RCJ Team· 15d ago
1 reply196 views
👍1
💬General
How Indiana Selected an RHTP Awardee: A Procurement Lesson
Indiana's RFP 26 87449 offers a useful lesson for organizations pursuing Rural Health Transformation Program work. Laurel Health Advisors was recommended for a five year, $860,088 teleconsult and telehealth landscape assessment—even though Sargad submitted the lowest cost finalist proposal. The decision turned on: • Management Assessment/Quality: 50 points • Cost: 30 points • Oral presentations and written responses • Project management and methodology credibility • Staffing, KPIs, state government experience, and AI approach • Certified MBE, WBE, and IVOSB subcontractor participation After oral presentations, Laurel's quality score increased from 42.75 to 44.25, while Sargad's fell from 24.50 to 19.50. Laurel ultimately scored 79.52 versus Sargad's 64.50. The takeaway: Indiana prioritized confidence in delivery over lowest price. A strong proposal needs more than a competitive budget—it needs a defensible methodology, named delivery team, measurable outcomes, relevant public sector experience, and a credible partner structure. Read the full RCJ case study: https://www.ruralcarejourney.com/reports/indiana awardee selection 2026 What are you seeing in other states—are technical quality and implementation credibility outweighing price in RHTP procurements?
RCJ Team· 17d ago
0 replies268 views
👍1
💬General
Partner Funding Opportunities
Grants, letters of intent, and technical assistance calls from universities, foundations, nonprofits, hospital associations, and tribal organizations — independent of, or aligned with, any single state's RHTP allocation. Tracked separately from our state by state RHTP opportunity tracker. A few things worth knowing if you haven't checked it out yet: Search, filter, and sort — search by keyword, filter by state (multi select), issuer type, and status, sort by due date or most recently added Submit an opportunity — signed in and know about a partner funded call we're missing? There's a "Submit an opportunity" button right on the page — drop the URL and we'll review and add it Cross linked with our main tracker — jump straight over to state by state RHTP procurement opportunities and back Check it out here: Partner Funding Opportunities
RCJ Team· 22d ago
0 replies410 views
👍1
💬General
Recap: Navigating the RHTP Ecosystem — Technology & Telehealth Opportunities
Thanks to everyone who joined Thursday's webinar — and to Solutionz and Telemedicine.com for co hosting. If you missed it (or want the highlights), here's a recap. The panel: Kristin Deprospero (Solutionz — AV/telehealth infrastructure, connected care, simulation technology), Eric Bacon (Telemedicine.com — end to end clinical telemedicine programs since 2008), and San Lee (Rural Care Journey). The big picture RHTP only works when four groups move together: funders, technology vendors, applicants/consultants, and the rural providers actually delivering care. Most state RFAs are landing with 2–3 week windows, which means the prep work — project concept, partners, budget, internal sign off — has to happen before the RFA drops, not after. A show of hands poll backed this up: 67% of attendees are still just exploring RHTP, 17% have applied, and 16% are already funded and implementing. Meanwhile states had roughly 52 days to build entire program structures around $200M in annual federal allocations — so readiness is lagging the timeline pressure. What actually makes telehealth programs work Eric's core warning: don't bolt on a new app that lives outside your existing EHR and clinical workflow. Technology that adds friction gets abandoned even when it's good tech. The fix is building a multidisciplinary implementation team — clinical, technical, operational, executive — before you pick a vendor, not after. Recurring high demand use cases across states: virtual specialty access, behavioral health, remote patient monitoring, EMS telehealth, care coordination, mobile care, and community health pods. RCJ platform walkthrough (Virginia example) San walked through how RCJ maps a state's RHTP landscape — Virginia's $190M federal allocation and $44M distributed across active opportunities, plus three tools: Eligibility Checker — surface compliance gaps against a state's specific requirements AI Narrative Assistant — reads an RFA and helps draft a proposal narrative aligned to it Vendor Matchmaker — matches a project narrative against RCJ's vendor directory ( 766 vendors at demo time) Also covered: filtering the vendor directory by state, technology vs. consulting vs. nonprofit/CBO, and capability fit. Open Clinic: rural EMS and OB access One of the more concrete discussions of the day — as rural hospitals close OB units, EMS crews increasingly handle emergency deliveries without easy access to specialist trainers. The idea floated: several smaller EMS agencies pooling resources for mobile simulation equipment, neonatal resuscitation mannequins, and shared traveling instructor / virtual specialist support, instead of each agency buying equipment it can't really afford alone. Virginia was named as facing the same OB desert problem. Where the money's going Three technology pillars keep showing up across state RHTP opportunities: 1. Remote care access — telehealth, virtual specialty care, mobile health, RPM 2. Connected clinical spaces — AV infrastructure, standardized telehealth rooms, device integration 3. IT foundations & cybersecurity — network modernization, EHR integration, interoperability, data exchange Winning the award is step one James Chapp (Ono Logic) made the point that an award is the start of the work, not the finish line — implementation capacity, workflow integration, and clinical adoption determine whether a funded project actually delivers. A second poll backed this up: attendees named defining project scope and timing/deadline pressure as their top two bottlenecks. For CAHs unsure where to start: pull together CEO, CMO, CFO, clinical, ops, and IT, and work backward from a real gap analysis — what problem, what outcome, what capability gap, what's actually allowable under your state's RFA — rather than picking a technology first. Takeaways Start building your team and partnerships before the RFA is released — the windows are too short to do it after. Let the clinical/operational problem drive technology selection, not the other way around. New systems need to plug into your existing EHR and workflows, or adoption stalls. A win is only as good as your ability to actually implement it. Regional/shared resourcing can put otherwise out of reach capability (simulation equipment, virtual specialists) within reach for smaller rural organizations. Want to keep the conversation going? Drop your state or your project bottleneck below — happy to point you at relevant open opportunities or vendors in the directory. Presenting organizations: Solutionz · Telemedicine.com
RCJ Team· 24d ago
0 replies232 views📎 1

👍1
💬General
New: Michigan RHTP GFO briefing — the first subrecipient list, by initiative
Michigan just published its first RHTP subrecipient list, and we've pulled it into a new live briefing on the Reports page: https://www.ruralcarejourney.com/reports/michigan rhtp gfo fy1 fy2 2026 What's in it How Michigan split its $173.1M Budget Period 1 award into five initiatives — Transforming Rural Health through Partnerships, Care Closer to Home Blueprint, Interoperability in Action, Workforce for Wellness, and the 5% Tribal carve out — and how the " 2026" vs " 2027" GFO records map to Budget Period 1 and Budget Period 2 (they're separate EGrAMS packages, not duplicates). The first subrecipient list, as ingested from MDHHS: $57.6M announced so far across 130 award rows to 118 organizations — roughly a third of the BP1 award — broken out by initiative. Every open BP2 GFO by deadline (the current wave clusters around Sept 11–19), plus the BP1 solicitations that already closed and are worth reading as application templates. A Michigan specific EGrAMS applicant checklist (non supplanting, HRSA rural service area, partnership evidence, the Oct 30 2026 BP1 obligation clock). One pattern worth flagging: the Partnerships initiative has the most awards (65) but not the most money — those average about $241K, versus Care Closer to Home's 17 awards averaging over $1M. The largest count of grants sits at roughly $76K–$83K each: community partners seeding a role inside someone else's partnership, not standalone awards. If you're a smaller rural organization, that's the realistic entry point — plan the partnership before you write the application. The live briefing is free to read for signed in members. There's also a paid deep dive PDF that adds the funded vs announced analysis per initiative, where the dollars concentrate (statewide intermediaries → regional hubs → the community partner long tail), the BP1→BP2 continuity read, and the positioning checklist. Questions about a specific Michigan fund or GFO — drop them here, or start a thread on the Questions board.
RCJ Team· 25d ago
0 replies16 views
👍1
💬General
Free Webinar: Technology & Telehealth Opportunities with RHTP Funding (Sept 10)
Solutionz, Inc. is hosting a free interactive webinar on technology, telehealth, connectivity, and infrastructure planning for RHTP initiatives — covering everything from project scoping to budgeting, procurement, and implementation readiness. When: Thursday, September 10, 2026, 2:00–3:00 PM ET (11:00 AM PT) Where: Online — anyone can view and join Register: https://events.teams.microsoft.com/event/e7cc1d64 3b02 4f3d 967e 5acf666626a8@21221911 5819 43de adcf d48d8e7f4999 Presenters: Kristin Deprospero, Strategic Sales Executive, Solutionz Eric Bacon, CEO, Telemedicine.com Bryan Arkwright, COO, Telemedicine.com San Lee, Rural Care Journey Expert Topics include: Technology and telehealth opportunities Connectivity and infrastructure planning Project scoping and technology requirements Budget planning and procurement considerations Program milestones, timelines, and implementation planning Project specific questions and guidance Who should attend: State and county health officials, rural hospitals and health systems, FQHCs, higher education and workforce development organizations, and IT/operations/finance/grant management teams working on RHTP funded initiatives. Both presenting organizations are in the RCJ vendor directory if you want to look at their broader capabilities first: Solutionz: https://www.ruralcarejourney.com/vendors/solutionz Telemedicine.com: https://www.ruralcarejourney.com/vendors/telemedicinecom
RCJ Team· 27d ago
0 replies50 views
👍1
💬General
Two new RCJ research reports — where Year 1 RHTP money landed, and who's ready for FY2
FY2 of the Rural Health Transformation Program begins October 1 — and we've just published two research reports to help you go into it with a clear, source checked picture. 📊 RHTP Awards Landscape Where Year 1 money actually landed: $3.587B across 1,538 selected award records and 1,012 distinct recipients in all 50 jurisdictions. Includes a state by state reconciliation analysis that flags where recorded totals run ahead of actual federal allocations, five in depth state profiles, and the Year 2 operating agenda. → Read the report New to RCJ? Start with the free companion infographic, Where the Money Landed : https://www.ruralcarejourney.com/reports/rhtp awards landscape infographic 2026 09 05 🧭 From First Year Funding to Lasting Rural Care — the FY1 → FY2 Outlook Which states are already ahead of the FY2 curve and which aren't: a dated 50 state evidence view, a taxonomy comparison across opportunities and awards, three verified state case studies (Kansas, Missouri, New York), and a concrete FY2 preparation checklist. → Read the report Both full PDFs are included with an RCJ membership , which also gets you the live 50 state opportunity tracker, deadline alerts, the vendor directory, and every prior research report. Become a member → and download both today.
RCJ Team· 28d ago
0 replies37 views
👍0
💬General
Find the real experts: new "Primary category only" filter on Vendors
Quick one for anyone browsing the vendor directory. We've added a "Primary category only" checkbox next to the capability filter on /vendors. Pick a category chip, flip it on, and the list drops every vendor for whom that category is just one of several tags they carry keeping only the ones for whom it's their actual main focus. The gap turned out bigger than expected: "Telehealth & Virtual Care" matches 273 vendors by tag, but only 57 actually have it as their primary category. The other 216 do it too, it's just not really what they're known for. It's live for everyone, not gated to Pro/Team. There's also a "Copy filter link" button if you want to hand a colleague a specific filtered view (e.g. primary only Telehealth vendors). https://www.ruralcarejourney.com/vendors
RCJ Team· 9/2/2026
1 reply115 views
👍3
💬General
Insights from RCJ’s First Informal Vendor Roundtable
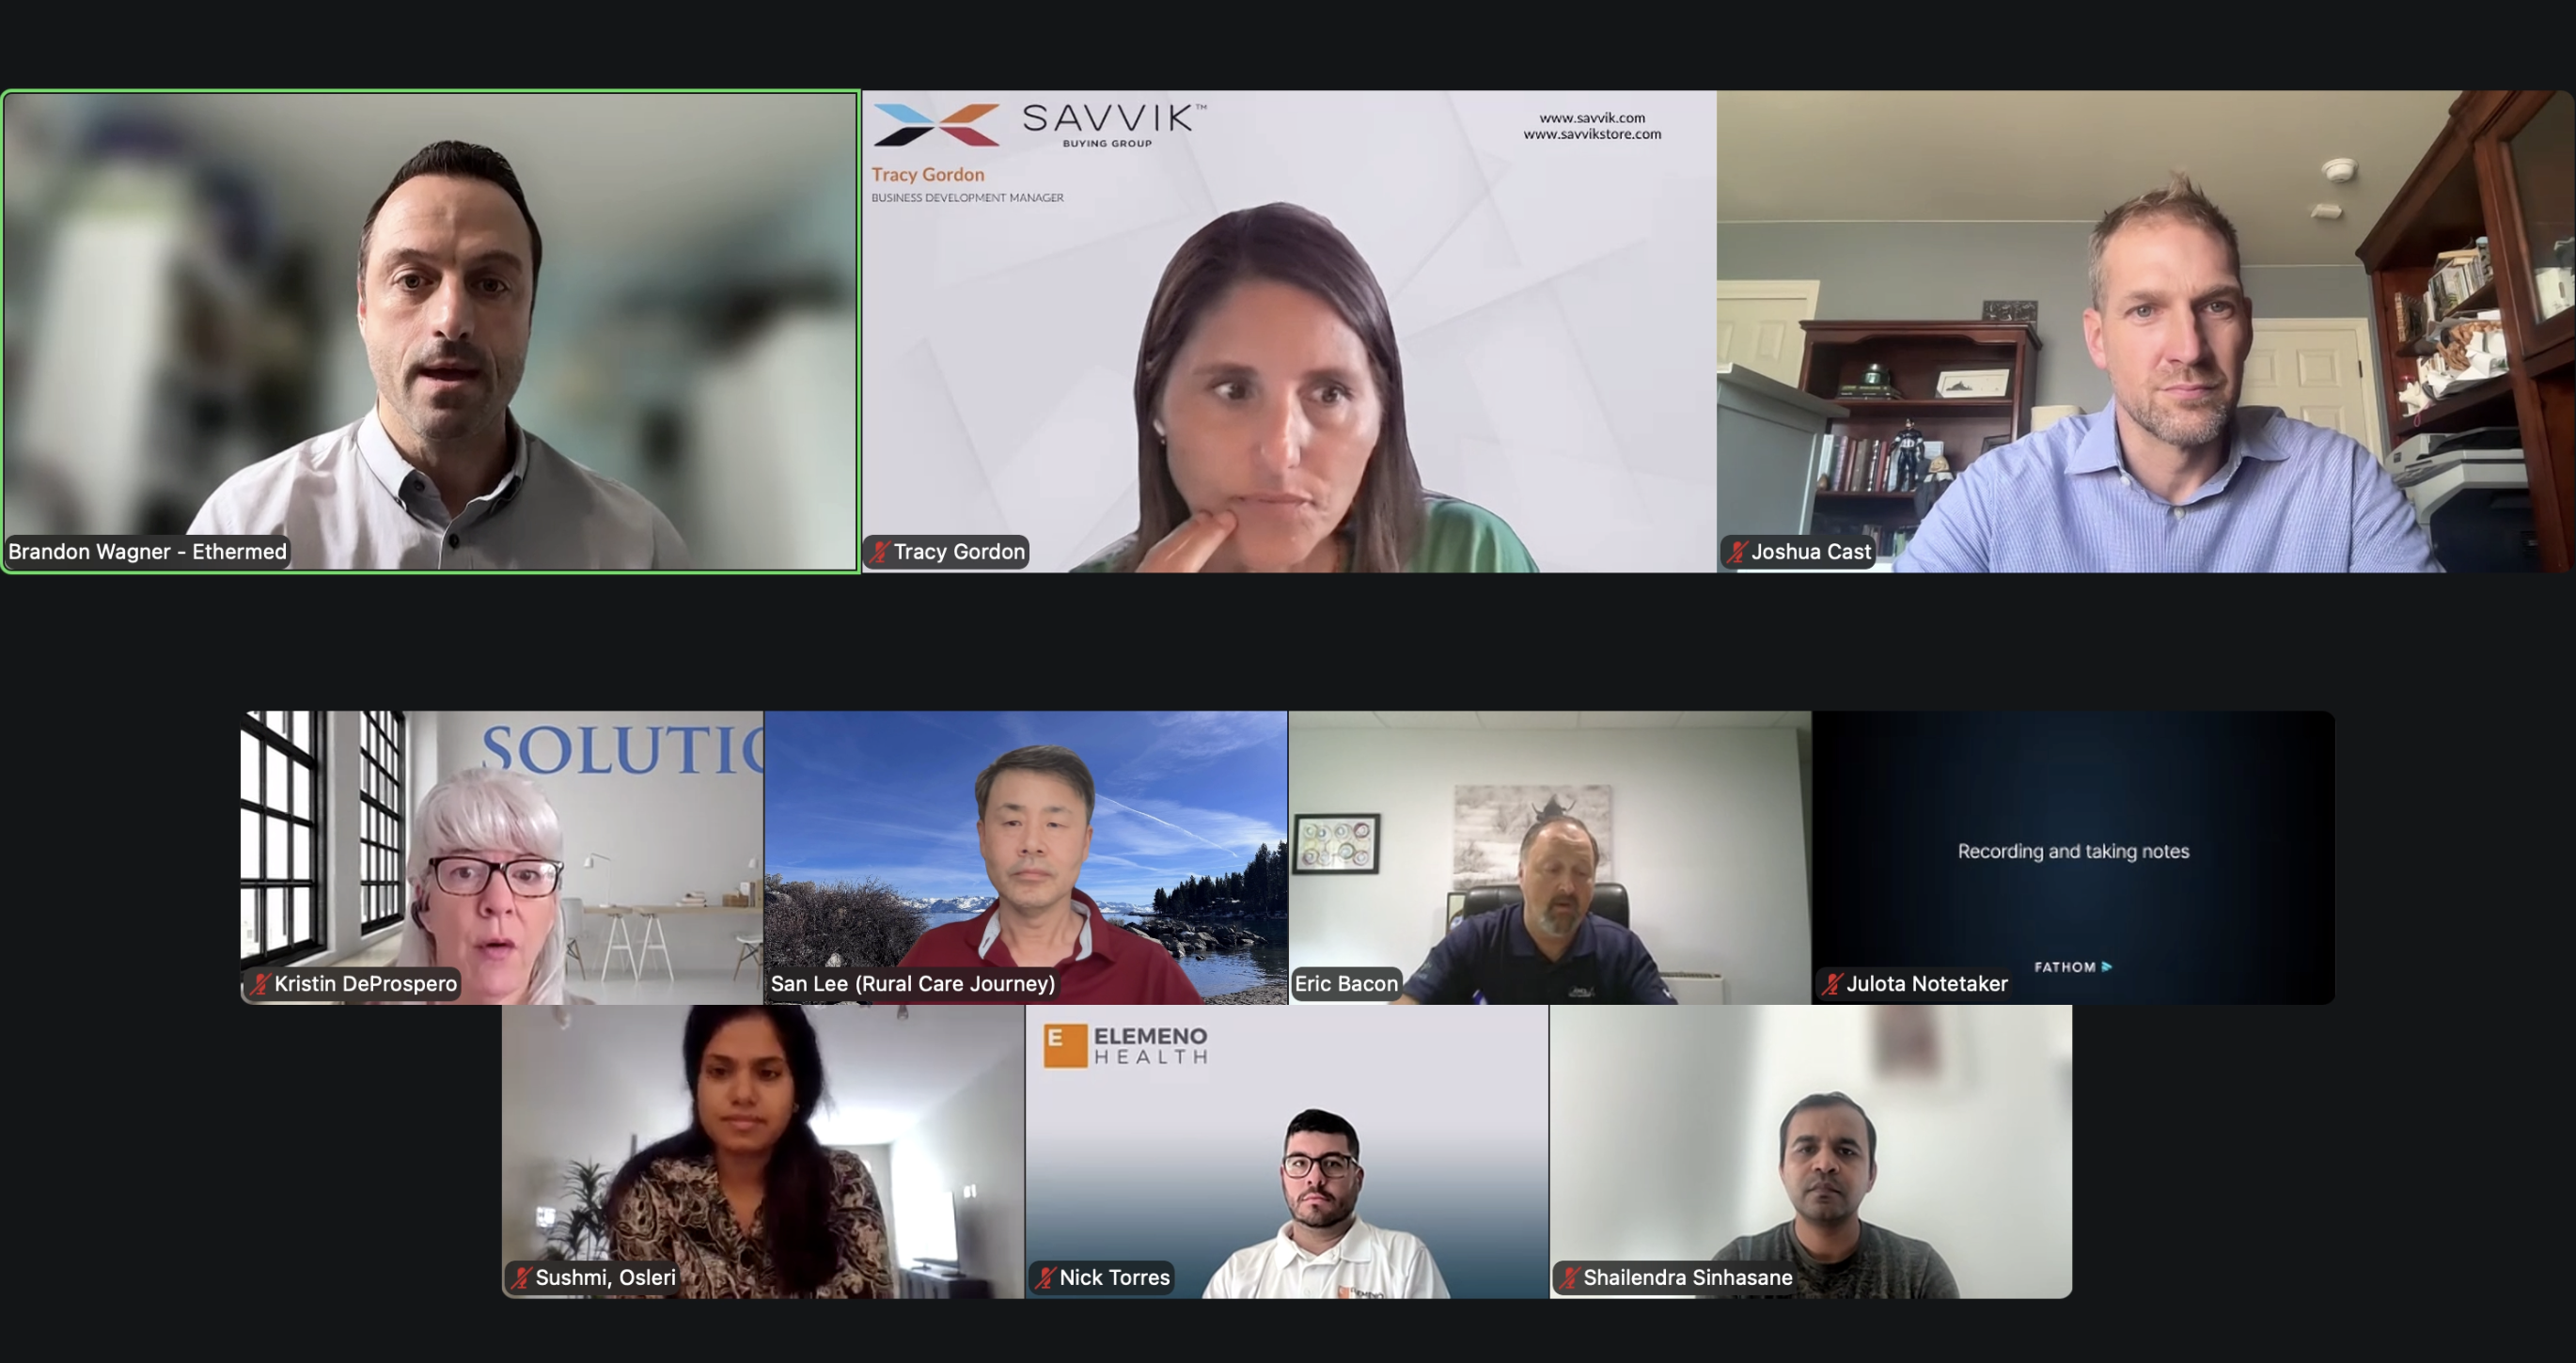
🎉 Congratulations — you secured the RHTP grant. Now what? That was the core question behind today’s Rural Care Journey Featured Vendor Roundtable. As RHTP moves from awards into implementation, the challenge changes quickly. It is no longer just: “How do we win the funding?” It becomes: “Who can actually help us deliver the program?” 🏥 Rural organizations may need technology, clinical services, workforce support, equipment, implementation partners, procurement expertise, and compliance support — often on very short timelines. 🤝 That is why RCJ is building more than a vendor directory. We are building an implementation ready network to help rural health organizations find best fit partners across telehealth, RPM, AI, interoperability, EMS, care coordination, equipment, workforce, behavioral health, chronic disease management, project implementation, procurement, and compliance. 💡 Today’s discussion reinforced an important point: Funding alone does not create transformation. Execution capacity does. 👏 Thank you to the leaders and teams who participated, representing organizations across the RCJ vendor community: Empowered Home, Savvik Buying Group, PowerTrain, Julota, AISAP, Elemeno Health, OnMed, Solutionz, Aquila Health, Predoc, EtherMed, eDermatology, Osleri, Telemedicine.com, Rainbow Health, GrandPad, and WellCheck. 🙏 Special thanks to Brandon Wagner, Tracy Gordon, Joshua Cast, Kristin DeProspero, Eric Bacon, Sushmi Kosuri, Nick Torres, Shailendra Sinasni, and Ayushi Patel for sharing their perspectives. 🧭 We also came away with practical priorities for RCJ: Better awardee intelligence Clearer vendor registration guidance Compliance and reporting timelines Improved program taxonomy Targeted alerts Stronger connections between vendors and implementation needs 🚀 The next phase of RHTP will not be defined only by who receives funding. It will be defined by who can turn that funding into something that actually works in rural communities. 🔎 Explore the RCJ Vendor Network: https://www.ruralcarejourney.com/vendors Winning the grant is the beginning. Implementation is where transformation happens.
RCJ Team· 8/29/2026
3 replies198 views📎 1
👍0
💬General
Most-viewed states and opportunities are now easier to explore
RCJ now highlights the most viewed states and opportunities on the dashboard. State cards show implementation status, total and active opportunities, awardees, and views. Opportunity cards include state, budget, due date, and views, with filters for Not closed and All. Each item links directly to its detail page.
RCJ Team· 8/26/2026
0 replies33 views
👍0
💬General
How to Prepare and Submit Your FY 2027 HRSA Health Center Program BPR (Step-by-Step Submission Guide)
This guide provides step by step instructions for Health Center Program (H80) award recipients to complete and submit their Fiscal Year (FY) 2027 Non Competing Continuation Budget Period Progress Report (BPR). Follow this manual to ensure your progress report is properly completed and submitted through the HRSA Electronic Handbooks (EHBs). Step 1: Verify Your Submission Window Your BPR module availability and final deadline in the EHBs are determined by your budget period start date. All submissions must be completed by 5:00 p.m. ET on the specified due date. Step 2: Complete EHBs Administrative Forms Log into the EHBs BPR module to review and complete the following embedded web forms: • SF PPR & SF PPR 2 Forms: Verify overall organizational details and primary project director information. • Key Contacts / Principal Form: Review all key personnel. Search every executive, board member, and project lead on SAM.gov to ensure they have active eligibility and are not debarred or excluded from federal funding. • Form 1C (Documents on File): Update the exact dates when key operational policies and administrative documents were last reviewed or revised. • Form 3 (Income Analysis): Enter projected non grant revenues for FY 2027. Break down expected income from patient services, third party reimbursements, state/local grants, and other operational revenue. • Forms 5A, 5B, and 5C (Scope Verification): Review these pre populated forms to confirm your current approved scope of project (Services Provided, Sites, and Specialty Services). (Note: These forms are for reference only in the BPR module; any updates require separate Change in Scope or Scope Adjustment submissions in EHBs). Step 3: Complete Project Narrative Updates Complete the narrative fields directly in EHBs. Each narrative section is strictly limited to 2,000 characters (approx. 300 words) and must cover FY 2026 progress to date, remaining goals, and projected changes for FY 2027: • Organizational Capacity: Address key operational developments, staff/executive vacancies, policy updates, and any active audit findings. If your health center received non compliance findings in a recent Operational Site Visit (OSV) or Service Area Competition (SAC), detail the corrective actions taken. • Patient Capacity: Summarize actual vs. projected patient counts across all major service lines (Medical, Dental, Mental Health, Substance Use Disorder, Vision, Support Services). If overall patient volume has dropped by more than 5% against projections, you must include a corrective action plan outlining specific steps to recover patient volume. Step 4: Assemble Financial Forms & Budget Narrative Attachment Your budget must cover total project costs (both requested federal grant funds and non federal program revenues): • SF 424A Form (Web Form): Enter requested federal funds (matching the pre populated amount from Item 33 of your most recent Notice of Award) and non federal funds across standard object class categories. • Line Item Budget Narrative (File Attachment): Upload a detailed breakdown for all cost categories. Step 5: Prepare Supplemental Award Updates (If Applicable) If your health center received BPHC supplemental funding since FY 2023 (including funds integrated into base awards), upload a narrative attachment under "Other Documents". Summarize progress and results using Uniform Data System (UDS) metrics (max 500 words per supplemental award). Step 6: Review Submission Rules & Perform Final EHBs Audit Before submitting, verify that your application meets all federal compliance rules: • Funding Distribution: Federal funding requests must be proportional across all existing program types (e.g., CHC, MHC, HCH, PHPC) as pre populated in EHBs. You cannot change total award amounts or shift funds between sub programs in the BPR. • Attachment Restrictions: EHBs limits document uploads. Ensure you only attach allowed files (Budget Narrative, Indirect Cost Rate Agreement, Supplemental Updates, and Proof of Non Profit Status Change if applicable). All other information must be entered directly into EHBs web forms. • Subrecipient Registrations: Confirm that all subrecipients or subaward contractors maintain an active SAM.gov registration and valid Unique Entity Identifier (UEI) number. • Final EHBs Review: Run the built in EHBs validation check to resolve missing fields or character count errors, then submit your progress report before the 5:00 p.m. ET deadline. To view the published article on our website, check out: https://alephgroupinc.com/fy 2027 hrsa bpr submission guide/ Disclaimer and Limitation of Liability This guide is provided by Aleph Group, Inc. for general informational purposes only and does not constitute official legal, financial, or regulatory compliance advice. Users are solely responsible for independently verifying all submission deadlines, form requirements, and guidelines directly with the HRSA Electronic Handbooks (EHBs) and official BPHC resources. Use of this guide does not guarantee grant approval or continued federal funding. To the fullest extent permitted by law, Aleph Group, Inc. disclaims all liability for any direct, indirect, or consequential damages including rejected submissions, grant delays, or loss of funding arising from or in connection with the use of or reliance on this material.
Aleph Group Inc.· 8/25/2026
Related: Small Rural Hospital Improvement Program Grants →
0 replies47 views
👍5
💬General
The Infrastructure Rural Health Transformation Cannot Afford to Overlook
Hello, RHT Community! As RHTP moves from planning to implementation, I have been thinking about a question that I hope we keep in the conversation: Who will sustain the transformation? We are making significant investments in access, technology, new care models, partnerships, and workforce pipelines. All are essential. But recruiting people into rural healthcare and creating the conditions that make them choose to stay are two different challenges. Transformation itself asks a lot of already stretched teams, new technology, new workflows, new partnerships, new expectations. That is why I opine workforce experience deserves a place in the implementation conversation. Turnover, vacancies, overtime, and contract labor tell us what has already happened. What if we also paid attention to what happens before someone leaves? Specifically: 1) Where are people becoming overloaded or isolated? 2) Where is trust strong or beginning to erode? 3) Who are the informal connectors holding teams together? 4) Where is critical knowledge concentrated in one or two people? In a rural organization, losing one person can mean much more than filling one vacancy. It can affect access, continuity, relationships, and sometimes an entire service. Five years from now, I hope we measure RHTP success not only by what we built, purchased, or launched, but also by what we strengthened. Technology is infrastructure. Facilities are infrastructure. People and relationships are infrastructure, too. I am curious what others are seeing. Where is workforce experience showing up in your RHTP implementation conversations and where might we still have a blind spot? Thank you! Sincerely, Ava
Ava Jones, PhD, MSM, RN· 8/24/2026
2 replies68 views
👍2
💬General
Year one progress
Deadline to obligate funds coming up quickly. How are you feeling about the program? Every state deploying differently has been fascinating. Thank goodness for RCJ!!
KDP· 8/21/2026
1 reply55 views