RCJ Community
Community
Ask questions, exchange implementation insights, and find collaborators across rural health transformation.
👍1
💬General
Two new RCJ research reports — where Year 1 RHTP money landed, and who's ready for FY2
FY2 of the Rural Health Transformation Program begins October 1 — and we've just published two research reports to help you go into it with a clear, source checked picture. 📊 RHTP Awards Landscape Where Year 1 money actually landed: $3.587B across 1,538 selected award records and 1,012 distinct recipients in all 50 jurisdictions. Includes a state by state reconciliation analysis that flags where recorded totals run ahead of actual federal allocations, five in depth state profiles, and the Year 2 operating agenda. → Read the report New to RCJ? Start with the free companion infographic, Where the Money Landed : https://www.ruralcarejourney.com/reports/rhtp awards landscape infographic 2026 09 05 🧭 From First Year Funding to Lasting Rural Care — the FY1 → FY2 Outlook Which states are already ahead of the FY2 curve and which aren't: a dated 50 state evidence view, a taxonomy comparison across opportunities and awards, three verified state case studies (Kansas, Missouri, New York), and a concrete FY2 preparation checklist. → Read the report Both full PDFs are included with an RCJ membership , which also gets you the live 50 state opportunity tracker, deadline alerts, the vendor directory, and every prior research report. Become a member → and download both today.
RCJ Team· 10h ago
0 replies22 views
👍0
💬General
Find the real experts: new "Primary category only" filter on Vendors
Quick one for anyone browsing the vendor directory. We've added a "Primary category only" checkbox next to the capability filter on /vendors. Pick a category chip, flip it on, and the list drops every vendor for whom that category is just one of several tags they carry keeping only the ones for whom it's their actual main focus. The gap turned out bigger than expected: "Telehealth & Virtual Care" matches 273 vendors by tag, but only 57 actually have it as their primary category. The other 216 do it too, it's just not really what they're known for. It's live for everyone, not gated to Pro/Team. There's also a "Copy filter link" button if you want to hand a colleague a specific filtered view (e.g. primary only Telehealth vendors). https://www.ruralcarejourney.com/vendors
RCJ Team· 5d ago
1 reply114 views
👍3
💬General
Insights from RCJ’s First Informal Vendor Roundtable
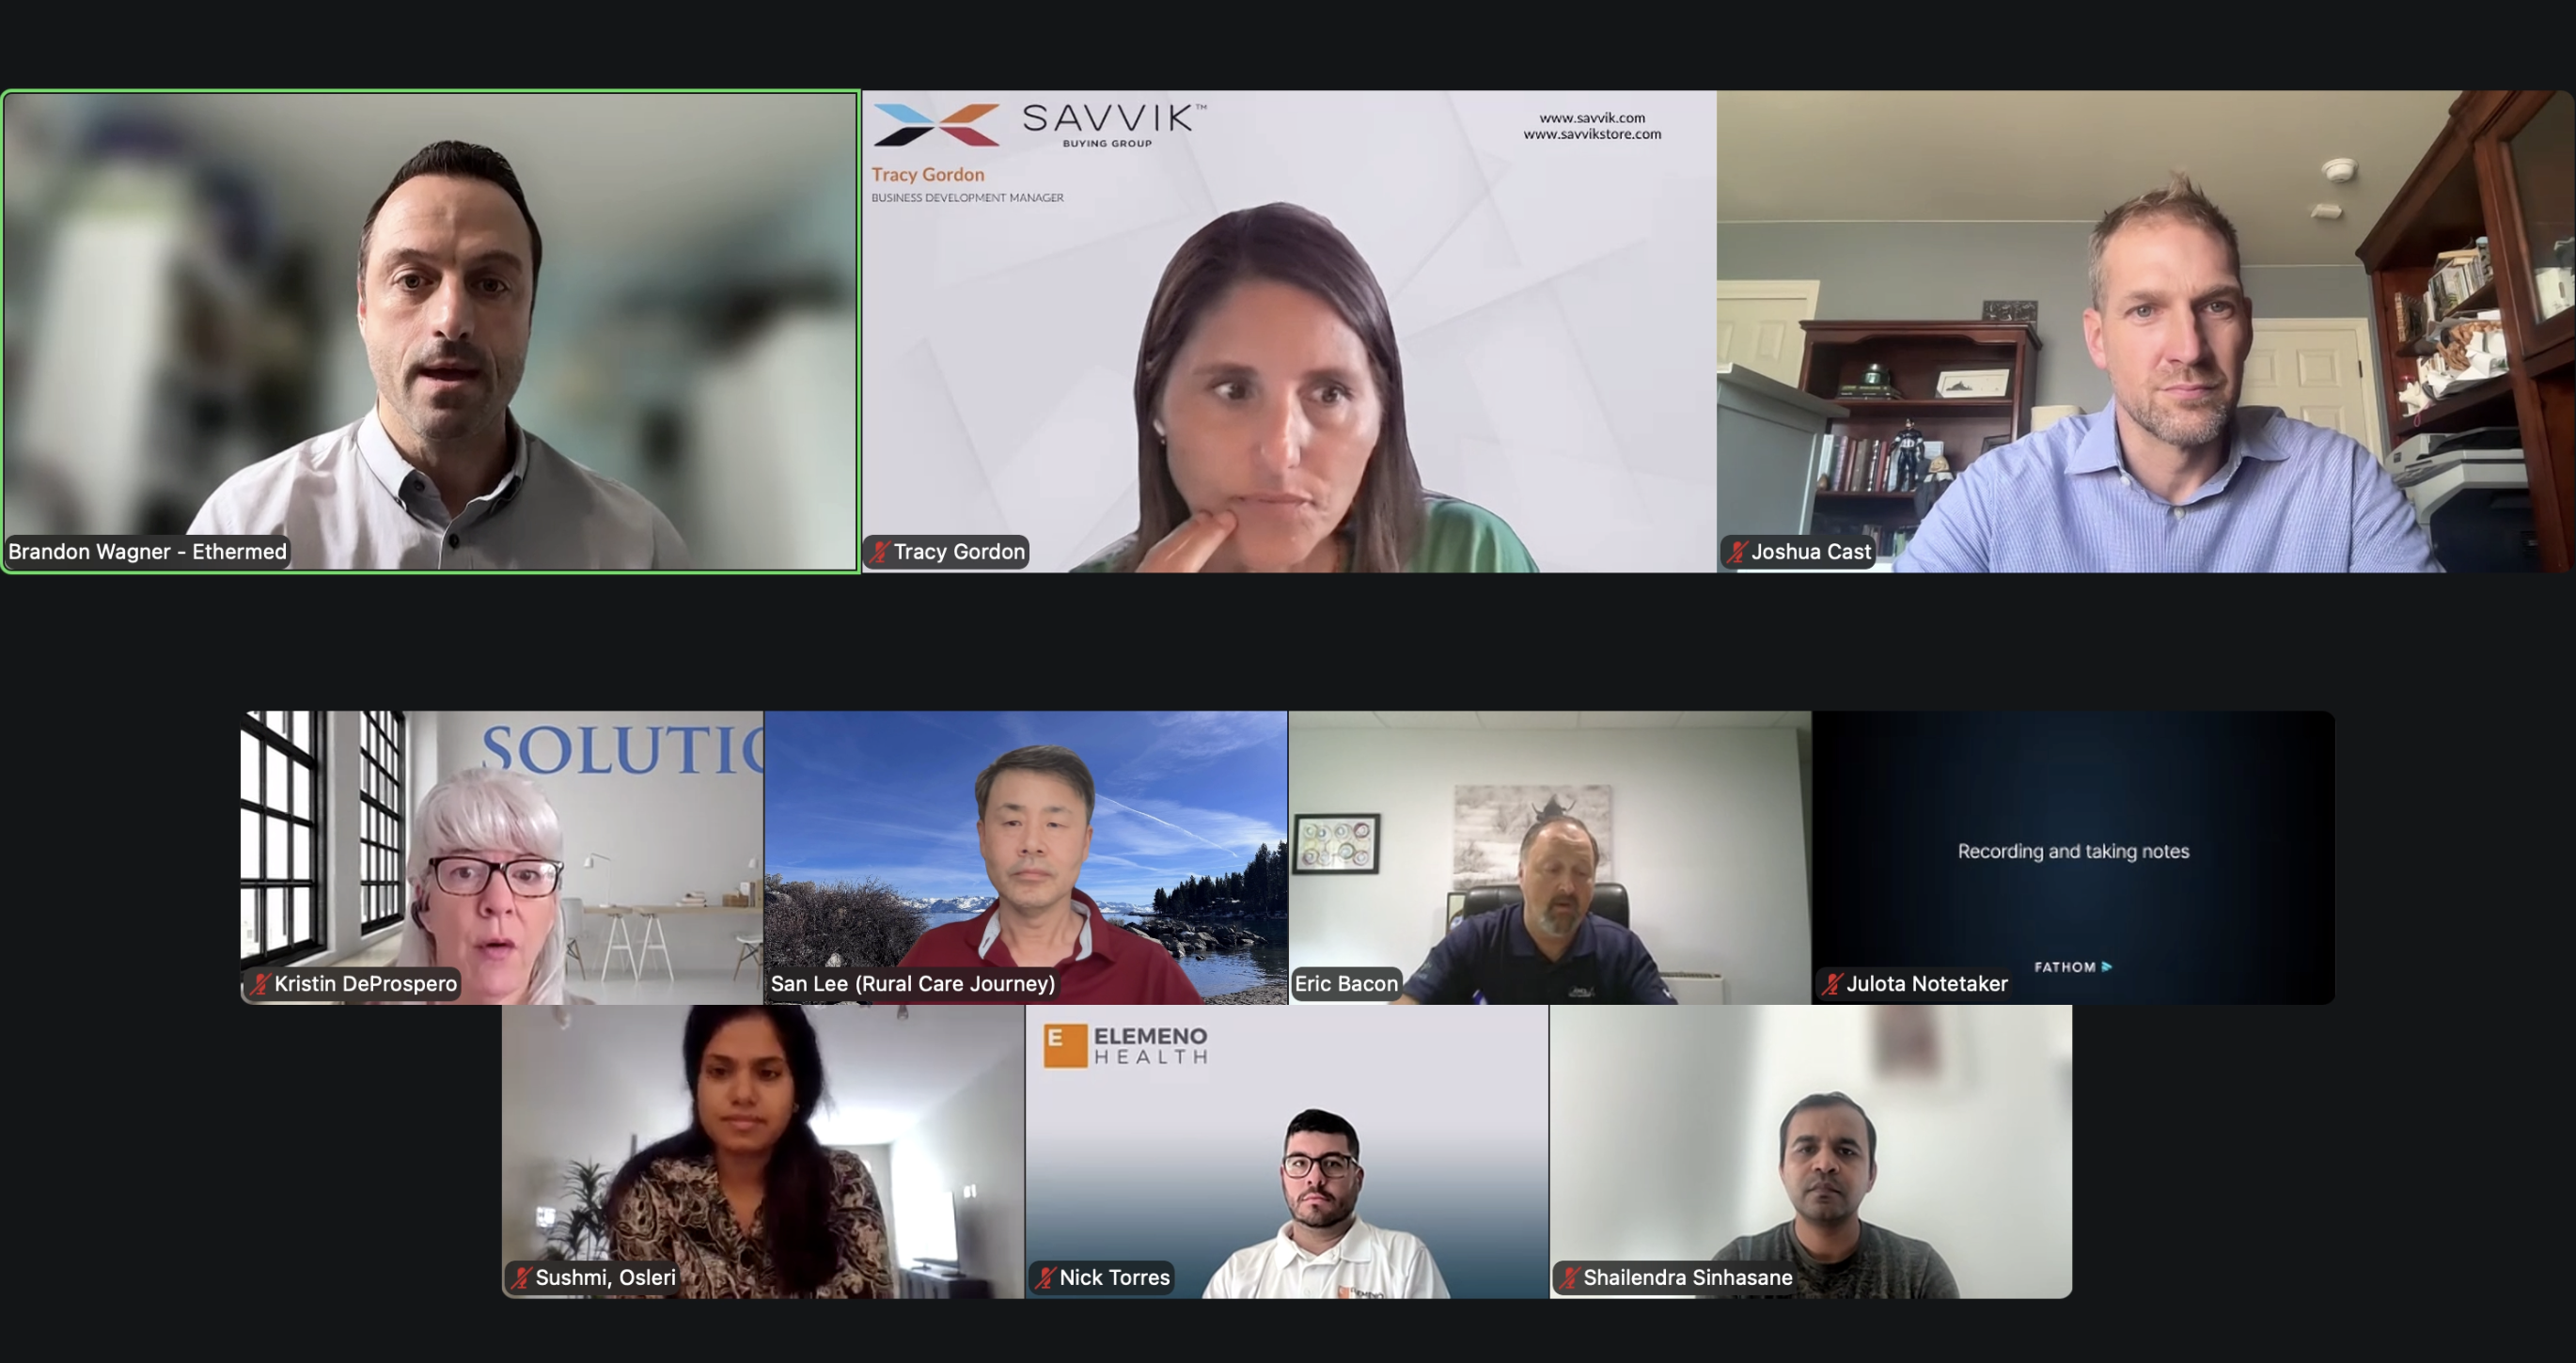
🎉 Congratulations — you secured the RHTP grant. Now what? That was the core question behind today’s Rural Care Journey Featured Vendor Roundtable. As RHTP moves from awards into implementation, the challenge changes quickly. It is no longer just: “How do we win the funding?” It becomes: “Who can actually help us deliver the program?” 🏥 Rural organizations may need technology, clinical services, workforce support, equipment, implementation partners, procurement expertise, and compliance support — often on very short timelines. 🤝 That is why RCJ is building more than a vendor directory. We are building an implementation ready network to help rural health organizations find best fit partners across telehealth, RPM, AI, interoperability, EMS, care coordination, equipment, workforce, behavioral health, chronic disease management, project implementation, procurement, and compliance. 💡 Today’s discussion reinforced an important point: Funding alone does not create transformation. Execution capacity does. 👏 Thank you to the leaders and teams who participated, representing organizations across the RCJ vendor community: Empowered Home, Savvik Buying Group, PowerTrain, Julota, Velocity Health, AISAP, Elemeno Health, OnMed, Solutionz, Aquila Health, Predoc, EtherMed, eDermatology, Osleri, Telemedicine.com, Rainbow Health, GrandPad, and WellCheck. 🙏 Special thanks to Brandon Wagner, Tracy Gordon, Joshua Cast, Kristin DeProspero, Eric Bacon, Sushmi Kosuri, Nick Torres, Shailendra Sinasni, and Ayushi Patel for sharing their perspectives. 🧭 We also came away with practical priorities for RCJ: Better awardee intelligence Clearer vendor registration guidance Compliance and reporting timelines Improved program taxonomy Targeted alerts Stronger connections between vendors and implementation needs 🚀 The next phase of RHTP will not be defined only by who receives funding. It will be defined by who can turn that funding into something that actually works in rural communities. 🔎 Explore the RCJ Vendor Network: https://www.ruralcarejourney.com/vendors Winning the grant is the beginning. Implementation is where transformation happens.
RCJ Team· 9d ago
3 replies168 views📎 1
👍0
💬General
Most-viewed states and opportunities are now easier to explore
RCJ now highlights the most viewed states and opportunities on the dashboard. State cards show implementation status, total and active opportunities, awardees, and views. Opportunity cards include state, budget, due date, and views, with filters for Not closed and All. Each item links directly to its detail page.
RCJ Team· 12d ago
0 replies32 views
👍0
💬General
How to Prepare and Submit Your FY 2027 HRSA Health Center Program BPR (Step-by-Step Submission Guide)
This guide provides step by step instructions for Health Center Program (H80) award recipients to complete and submit their Fiscal Year (FY) 2027 Non Competing Continuation Budget Period Progress Report (BPR). Follow this manual to ensure your progress report is properly completed and submitted through the HRSA Electronic Handbooks (EHBs). Step 1: Verify Your Submission Window Your BPR module availability and final deadline in the EHBs are determined by your budget period start date. All submissions must be completed by 5:00 p.m. ET on the specified due date. Step 2: Complete EHBs Administrative Forms Log into the EHBs BPR module to review and complete the following embedded web forms: • SF PPR & SF PPR 2 Forms: Verify overall organizational details and primary project director information. • Key Contacts / Principal Form: Review all key personnel. Search every executive, board member, and project lead on SAM.gov to ensure they have active eligibility and are not debarred or excluded from federal funding. • Form 1C (Documents on File): Update the exact dates when key operational policies and administrative documents were last reviewed or revised. • Form 3 (Income Analysis): Enter projected non grant revenues for FY 2027. Break down expected income from patient services, third party reimbursements, state/local grants, and other operational revenue. • Forms 5A, 5B, and 5C (Scope Verification): Review these pre populated forms to confirm your current approved scope of project (Services Provided, Sites, and Specialty Services). (Note: These forms are for reference only in the BPR module; any updates require separate Change in Scope or Scope Adjustment submissions in EHBs). Step 3: Complete Project Narrative Updates Complete the narrative fields directly in EHBs. Each narrative section is strictly limited to 2,000 characters (approx. 300 words) and must cover FY 2026 progress to date, remaining goals, and projected changes for FY 2027: • Organizational Capacity: Address key operational developments, staff/executive vacancies, policy updates, and any active audit findings. If your health center received non compliance findings in a recent Operational Site Visit (OSV) or Service Area Competition (SAC), detail the corrective actions taken. • Patient Capacity: Summarize actual vs. projected patient counts across all major service lines (Medical, Dental, Mental Health, Substance Use Disorder, Vision, Support Services). If overall patient volume has dropped by more than 5% against projections, you must include a corrective action plan outlining specific steps to recover patient volume. Step 4: Assemble Financial Forms & Budget Narrative Attachment Your budget must cover total project costs (both requested federal grant funds and non federal program revenues): • SF 424A Form (Web Form): Enter requested federal funds (matching the pre populated amount from Item 33 of your most recent Notice of Award) and non federal funds across standard object class categories. • Line Item Budget Narrative (File Attachment): Upload a detailed breakdown for all cost categories. Step 5: Prepare Supplemental Award Updates (If Applicable) If your health center received BPHC supplemental funding since FY 2023 (including funds integrated into base awards), upload a narrative attachment under "Other Documents". Summarize progress and results using Uniform Data System (UDS) metrics (max 500 words per supplemental award). Step 6: Review Submission Rules & Perform Final EHBs Audit Before submitting, verify that your application meets all federal compliance rules: • Funding Distribution: Federal funding requests must be proportional across all existing program types (e.g., CHC, MHC, HCH, PHPC) as pre populated in EHBs. You cannot change total award amounts or shift funds between sub programs in the BPR. • Attachment Restrictions: EHBs limits document uploads. Ensure you only attach allowed files (Budget Narrative, Indirect Cost Rate Agreement, Supplemental Updates, and Proof of Non Profit Status Change if applicable). All other information must be entered directly into EHBs web forms. • Subrecipient Registrations: Confirm that all subrecipients or subaward contractors maintain an active SAM.gov registration and valid Unique Entity Identifier (UEI) number. • Final EHBs Review: Run the built in EHBs validation check to resolve missing fields or character count errors, then submit your progress report before the 5:00 p.m. ET deadline. To view the published article on our website, check out: https://alephgroupinc.com/fy 2027 hrsa bpr submission guide/ Disclaimer and Limitation of Liability This guide is provided by Aleph Group, Inc. for general informational purposes only and does not constitute official legal, financial, or regulatory compliance advice. Users are solely responsible for independently verifying all submission deadlines, form requirements, and guidelines directly with the HRSA Electronic Handbooks (EHBs) and official BPHC resources. Use of this guide does not guarantee grant approval or continued federal funding. To the fullest extent permitted by law, Aleph Group, Inc. disclaims all liability for any direct, indirect, or consequential damages including rejected submissions, grant delays, or loss of funding arising from or in connection with the use of or reliance on this material.
Aleph Group Inc.· 13d ago
Related: Small Rural Hospital Improvement Program Grants →
0 replies25 views
👍0
❓Q&A✓ Answered
Can I manage how many emails I receive from RCJ?
Feel like you are getting too many emails from RCJ? Is there any way to manage the number of emails I receive? I would like to keep the updates that matter most without opting out of everything.
Anonymous· 13d ago
1 reply18 views
👍5
💬General
The Infrastructure Rural Health Transformation Cannot Afford to Overlook
Hello, RHT Community! As RHTP moves from planning to implementation, I have been thinking about a question that I hope we keep in the conversation: Who will sustain the transformation? We are making significant investments in access, technology, new care models, partnerships, and workforce pipelines. All are essential. But recruiting people into rural healthcare and creating the conditions that make them choose to stay are two different challenges. Transformation itself asks a lot of already stretched teams, new technology, new workflows, new partnerships, new expectations. That is why I opine workforce experience deserves a place in the implementation conversation. Turnover, vacancies, overtime, and contract labor tell us what has already happened. What if we also paid attention to what happens before someone leaves? Specifically: 1) Where are people becoming overloaded or isolated? 2) Where is trust strong or beginning to erode? 3) Who are the informal connectors holding teams together? 4) Where is critical knowledge concentrated in one or two people? In a rural organization, losing one person can mean much more than filling one vacancy. It can affect access, continuity, relationships, and sometimes an entire service. Five years from now, I hope we measure RHTP success not only by what we built, purchased, or launched, but also by what we strengthened. Technology is infrastructure. Facilities are infrastructure. People and relationships are infrastructure, too. I am curious what others are seeing. Where is workforce experience showing up in your RHTP implementation conversations and where might we still have a blind spot? Thank you! Sincerely, Ava
Ava Jones, PhD, MSM, RN· 14d ago
2 replies61 views
👍1
❓Q&A✓ Answered
Can RCJ alert me when a new opportunity matches a keyword I care about?
Can RCJ alert me when a new opportunity matches a keyword I care about?
Anonymous· 15d ago
1 reply24 views
👍2
💬General
Year one progress
Deadline to obligate funds coming up quickly. How are you feeling about the program? Every state deploying differently has been fascinating. Thank goodness for RCJ!!
KDP· 17d ago
1 reply53 views
👍0
💎Insider
Member-only discussion
Sign in to view this member-only discussion.
👍0
💎Insider
Member-only discussion
Sign in to view this member-only discussion.
👍0
🤝Collab
Member-only discussion
Sign in to view this member-only discussion.
👍0
🤝Collab
Member-only discussion
Sign in to view this member-only discussion.
👍0
💎Insider
Member-only discussion
Sign in to view this member-only discussion.